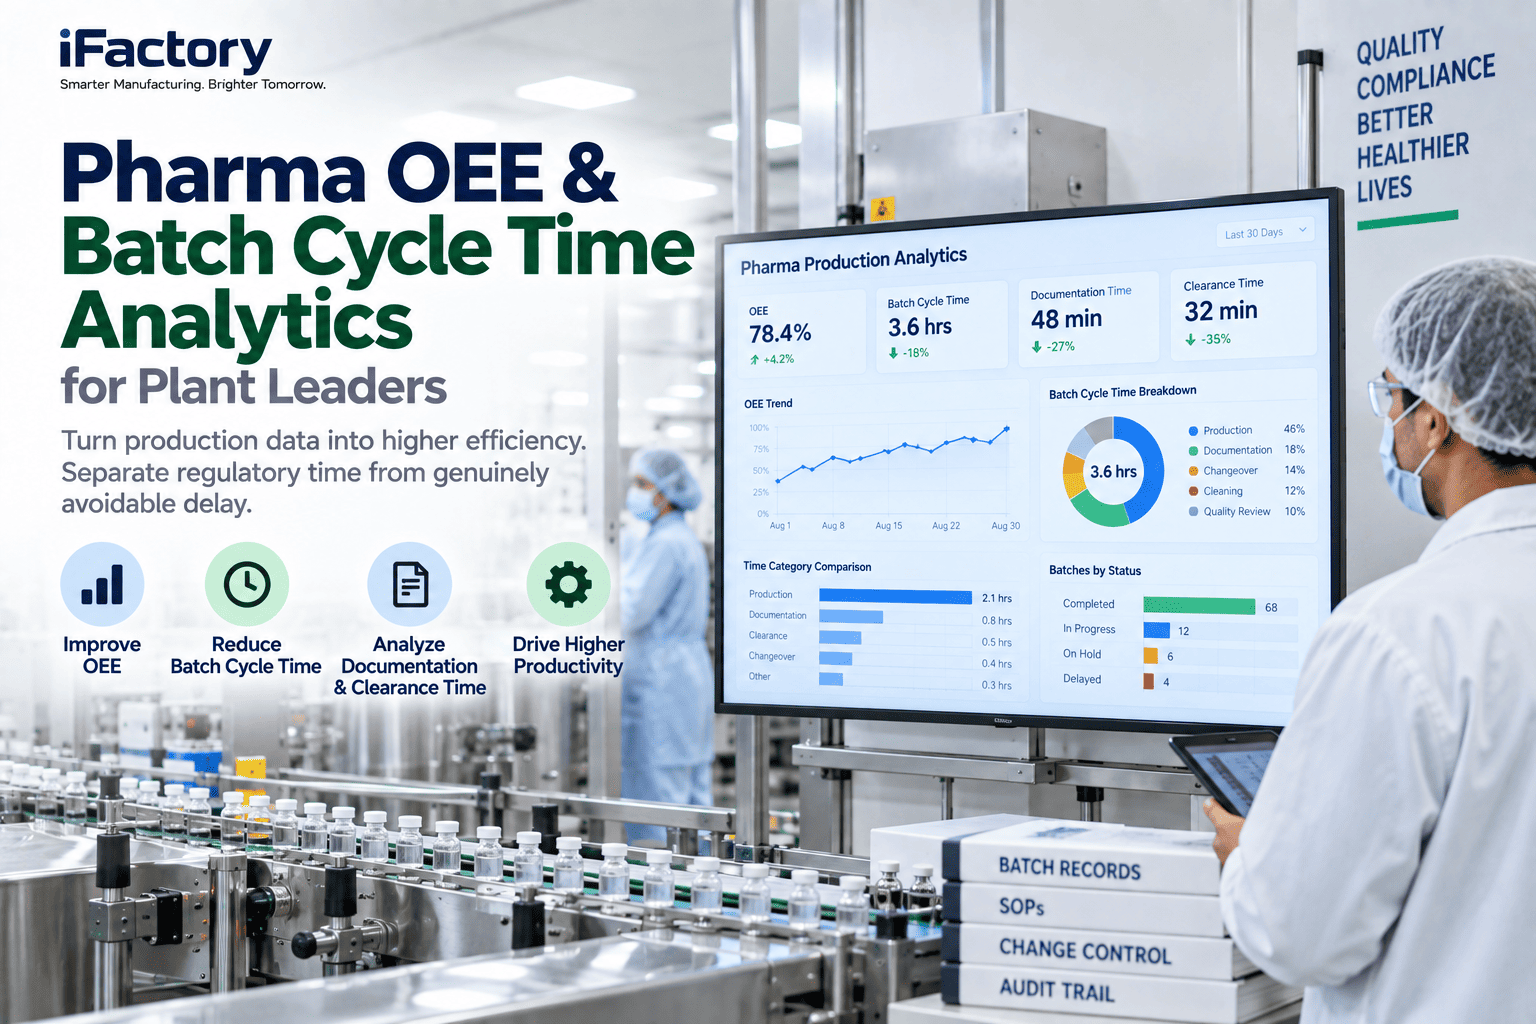
Pharma OEE benchmarks look nothing like automotive or general discrete manufacturing, and treating them as if they should is where most improvement programs fail. Benchmark studies place median sterile-line OEE around 23% with top-performing sites near 49% and pharma world-class in the 65-75% band — because between-batch cleaning, equipment qualification reconfirmation, in-process testing, and batch record documentation are structural time buckets GMP requires, not waste to be eliminated. Meaningful pharma OEE analytics separate regulatory time (structural, non-recoverable) from documentation lag and equipment unreliability (recoverable). What plant leaders need is not a scoreboard against automotive benchmarks — it is the discipline that tells them exactly which fraction of each batch cycle is genuinely avoidable.
iFactory / Pharma OEE for plant leaders
Separate Structural Regulatory Time from Avoidable Delay — Every Batch, Every Line
Pharma-specific OEE analytics with ISO 22400-2 loss decomposition, batch cycle time separated into value-add, structural regulatory, documentation lag, and breakdown investigation — so improvement effort targets the fraction that is actually recoverable.
Documentation / clearance
Breakdown & investigation
ISO 22400-2
loss decomposition
Regulatory vs
avoidable time
Sterile · OSD
line-type calibrated
The Problem in Pharma OEE Practice
A typical pharma plant reports an OEE number monthly to corporate leadership. It sits between 30% and 55%, gets compared against a benchmark aspiration of 70% or 85% pulled from a general manufacturing reference, and generates a cyclical conversation about why pharma cannot hit automotive numbers. The conversation misses the point. Pharma OEE below 50% is not the failure — the mis-framing of it as failure is. Benchmark studies place median sterile-line OEE around 23% with top performers at 49%; oral solid dose lines run higher but rarely hit discrete-manufacturing bands. The corporate report doesn't tell the plant leader which fraction of shortfall is structural versus recoverable.
Where Pharma Cycle Time Actually Bleeds
Pharma batch cycle time loss modes are well-documented. Each one has a recoverable fraction — but only if the analytics separate it from structural regulatory time.
Documentation lag
Manufacturing execution delays of 15-45 minutes between batch steps as operators complete paper batch records. Accumulated across multi-step processes, cuts overall line efficiency by 8-15%. Electronic batch records recover most of it.
Line clearance drift
Line clearance activities that should follow SMED principles run at unstandardised times. Same clearance takes 45 minutes one shift, 75 the next — because nobody measured the variance or attacked its causes.
IPC-triggered stops
Tablet weight variation, capsule fill uniformity, or dissolution test failures halt production 30-90 minutes per event. Facilities running 50-100 batches monthly see 15-25 such stops — up to 40 hours of monthly downtime.
Reliability-driven deviations
Unplanned equipment failure mid-batch triggers not only downtime but deviation investigation, disposition decision, and CAPA — costs that compound far beyond the downtime itself. Condition-based maintenance shifts the equation.
What Good Looks Like in Pharma OEE
A working pharma OEE system holds four disciplines together — line-type-appropriate benchmarks, ISO 22400-2 loss decomposition, batch time separation by category, and improvement targeted at the recoverable fraction.
Realistic Benchmarks
Benchmarks calibrated to line type — sterile injectable, oral solid dose, biologics, packaging — not the automotive 85% imported from a corporate template. Improvement targets that operators can trust.
Calibrated, not imported
ISO 22400 Decomposition
ISO 22400-2 loss categories applied so cleaning, changeover, line clearance, documentation, and unplanned downtime each measure separately. Changeover becomes the SMED target once it is visible on its own.
Category-separated
Batch Time Anatomy
Every batch cycle broken into value-add, structural regulatory, documentation lag, breakdown investigation. Aggregate view for plant leaders; drill-down for line supervisors on any specific loss.
Anatomy every batch
Recoverable Focus
Improvement effort steered at the recoverable fraction — documentation via EBR integration, reliability via condition-based maintenance, clearance via SMED. Structural fraction acknowledged and left alone.
Effort where it moves
How iFactory AI Fits
iFactory AI overlays your MES (Werum PAS-X, Rockwell PharmaSuite, Emerson Syncade), LIMS (LabWare, LabVantage, STARLIMS), and equipment historians — reading events and durations, applying ISO 22400-2 categorisation, and producing the batch-time anatomy your operations directors can actually act on.
Loss Decomposer
OEE Layer
ISO 22400-2 loss categories automatically classified from MES event and equipment historian data. Cleaning, changeover, clearance, documentation, and breakdown measured as separate categories per line.
Line Benchmarks
OEE + Analytics
Benchmarks per line type (sterile, OSD, biologics, packaging) with world-class and top-quartile bands. Gap to next quartile calculated as the recoverable-fraction opportunity.
Batch Anatomy
OEE + MES
Every batch cycle decomposed into value-add, structural, documentation, breakdown time. Trend and outlier analysis across lines, products, and shifts.
EBR Bridge
OEE + eBR
Integration with electronic batch record systems that eliminates paper-driven documentation lag. Where paper EBR remains, the lag is measured explicitly so the business case for eBR is visible.
Ask your operations director to produce last quarter's OEE number split into value-add, structural regulatory, documentation lag, and breakdown investigation. If the answer is one aggregate number without the split, the improvement conversation cannot land where the recoverable fraction actually is. Book a pharma OEE review.
12-Week Pharma OEE Pilot on One Line
One sterile, OSD, or packaging line, twelve weeks. The pilot deploys ISO 22400-2 decomposition, produces the first honest batch anatomy, and identifies the specific recoverable fraction to attack next.
Weeks 1–3
Baseline + Anatomy
Baseline current OEE reporting. Load line and product configuration. Apply ISO 22400-2 decomposition to the last 20 batches. First honest batch anatomy produced.
Weeks 4–7
MES + Historian
MES event capture and equipment historian integration live. Documentation lag, clearance duration, and IPC-stop patterns measured continuously — not from sample.
Weeks 8–10
Target Set
Recoverable fraction quantified per line. Top-3 loss categories with SMED, EBR-integration, or condition-based-maintenance targets. Improvement plan owned by named leaders.
Weeks 11–12
Rollout Ready
First-line pilot cycle closes with quantified recovery. Rollout to remaining lines and to sister sites scoped based on where the recoverable fraction is largest.
Who Owns the KPI
Pharma OEE crosses operations, quality, maintenance, and site leadership. Each function owns a specific KPI or the OEE conversation stays at the corporate report level.
Operations Director
Recoverable OEE gap closed
Owns the site outcome — the recoverable-fraction gap between current OEE and top-quartile line-type benchmark. Structural fraction excluded from the conversation.
Production Manager
Documentation lag per batch
Owns the front-line recovery — batch documentation time trending down. eBR integration or workflow changes that remove 15-45 min lag between steps.
Maintenance Lead
Unplanned downtime causing deviation
Owns the reliability outcome — unplanned equipment failures that trigger deviation investigations. Condition-based maintenance moves reactive failure to planned action.
QA Lead
IPC-triggered line stops per month
Owns the in-process outcome — IPC stops that are genuine quality signals vs those that reflect process instability. Real signals stay; noise gets engineered out.
FAQ
How does this handle sterile injectables specifically — the OEE floor is so much lower?
Sterile injectable lines carry the most stringent structural burden — aseptic setup, environmental monitoring, media-fill qualifications, extended cleaning cycles between batches — which is exactly why the median benchmark sits around 23% and top performers around 49%. The pharma OEE workflow calibrates benchmarks specifically for sterile line types and separates the structural burden explicitly so improvement conversations focus on the 20-30 percentage-point recoverable gap rather than an impossible gap to automotive benchmarks. Where isolator or RABS technology reduces environmental setup time, that shifts the structural floor and the benchmark moves with it.
What about ISO 22400 — is that the right framework, or should we use TEEP or NEE?
ISO 22400 Part 2 defines the KPIs used in manufacturing operations management and is the most widely-adopted framework for consistent, comparable loss measurement across sites. It defines availability, performance, and quality losses with sufficient granularity to separate cleaning, changeover, clearance, and unplanned downtime — which is exactly what pharma needs. TEEP (Total Effective Equipment Performance) adds schedule loss to OEE, useful for capacity conversations but less useful for operational improvement. NEE (Net Equipment Effectiveness) narrows to unplanned downtime, useful for reliability but incomplete. Most pharma sites benefit from ISO 22400 as the primary framework with TEEP as a capacity overlay.
Book a demo to see the loss decomposition on your line data.
How does this integrate with our existing MES (PAS-X, PharmaSuite, Syncade)?
The overlay reads events from your MES rather than replacing it. Werum PAS-X, Rockwell PharmaSuite, Emerson Syncade, and Siemens Opcenter Execution Pharma all expose batch step events, phase durations, and IPC results through documented APIs. The overlay reads those events, applies ISO 22400-2 loss categorisation, and produces the batch time anatomy without adding operator burden or requiring MES revalidation. Where documentation lag is currently driven by paper batch records alongside the MES, the overlay measures the lag explicitly — providing the business case for full eBR conversion. What you get is the analytics view MES reports rarely produce; what you keep is your validated MES.
Stop comparing pharma OEE against automotive benchmarks.
Decompose One Line's Batch Cycle Time — Live
Bring last quarter's batch records and MES event data from one line. We'll apply ISO 22400-2 decomposition, produce the batch anatomy, and quantify the specific recoverable fraction that improvement effort should target.
Recoverable
fraction targeted